Ringworm on Skin Versus Scalp Visual Differences
Hair shafts explain why scalp ringworm looks nothing like body ringworm.
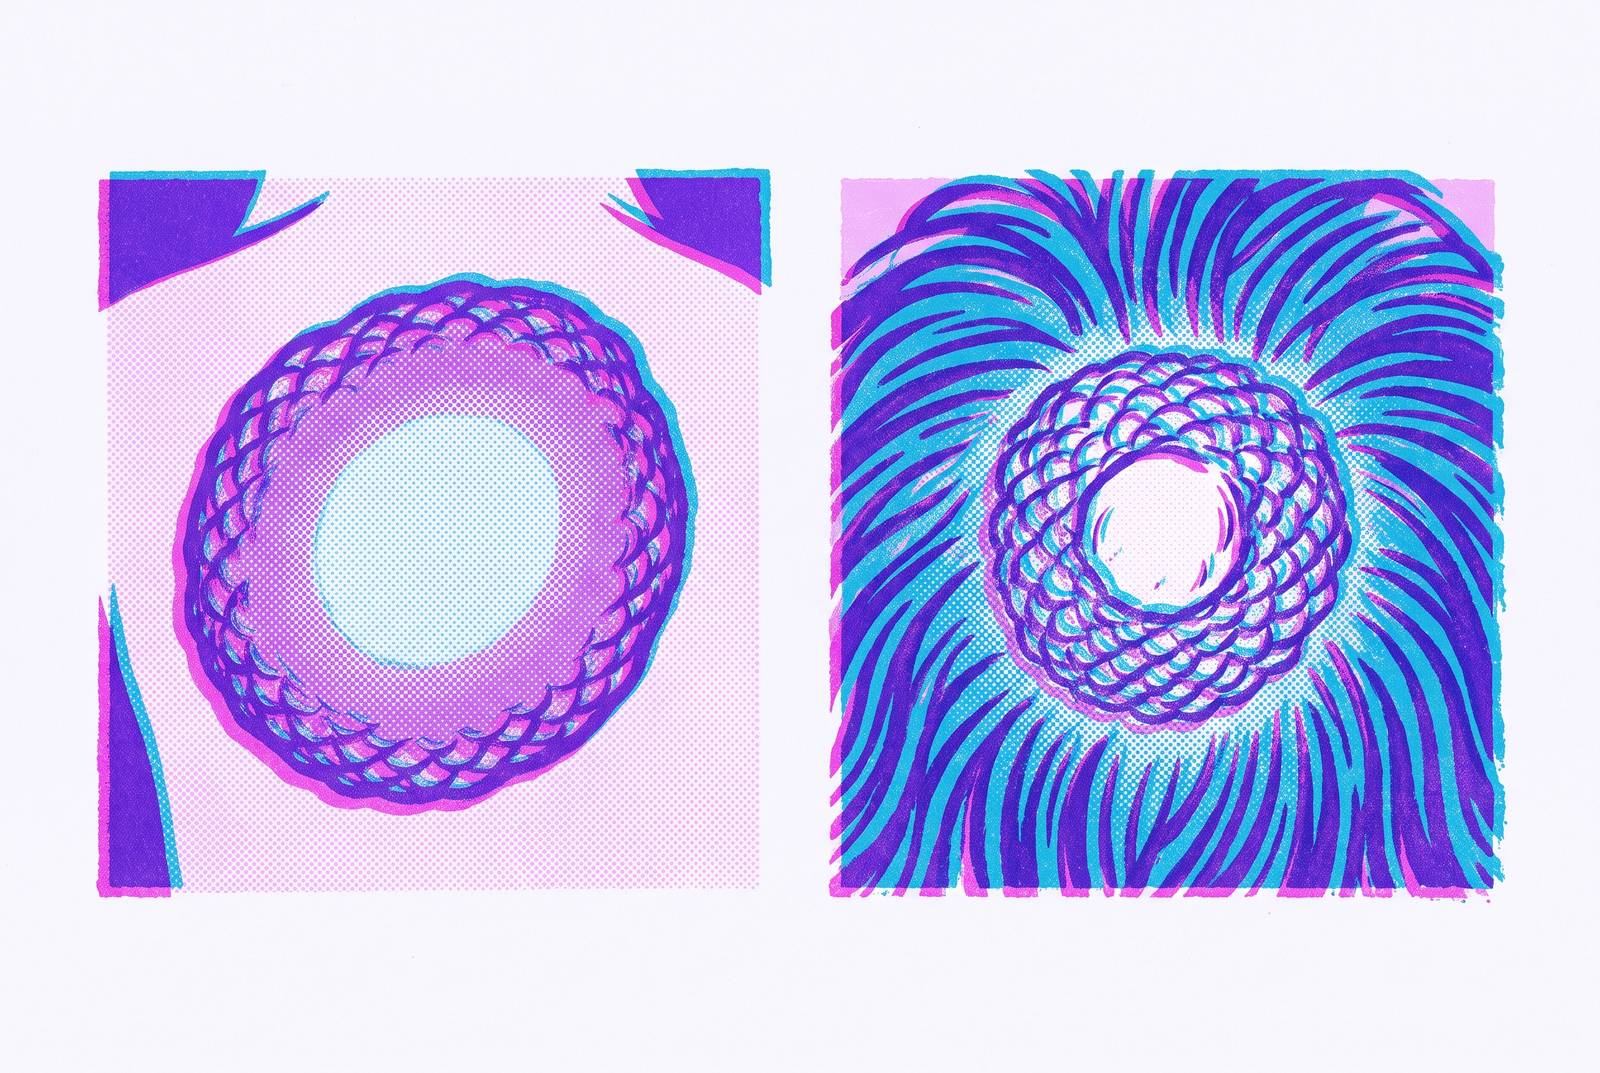
Ringworm changes its appearance dramatically depending on where it lands, and the reason comes down to a single anatomical fact: hair shafts are involved on the scalp and absent on bare skin. That difference in terrain reshapes almost everything about how the infection looks, spreads, and gets treated. Because the wrong assumption can delay the right care, knowing which version is staring back from the mirror (or from a kid's scalp at pickup) affects how quickly someone gets proper treatment. This piece looks at Ringworm on Skin Versus Scalp Visual Differences.
Why ringworm is named for a shape it sometimes barely makes
No worm causes ringworm. The name comes from the circular lesion shape that early observers noticed, back when a curled shape under the skin looked enough like a parasite to earn the label. But the shape that gave the infection its name is not universal. Ringworm on the face, scalp, or groin often skips the tidy circle entirely, which means anyone searching for a perfect ring might walk right past an active infection.
The scale of this condition demands a second look. Ringworm makes up roughly half of an estimated 650 million fungal skin infections worldwide, and in some countries more than a quarter of children under 10 carry a scalp infection specifically WHO CDC Liv Hospital. This is a common, widespread diagnosis. It is common enough that most people will encounter it, directly or through a child, at some point.
Drug-resistant strains of the fungi behind ringworm have been spreading from South-East Asia into the Middle East, Europe, Africa, and the Americas. That single fact raises the stakes on getting identification and treatment right, rather than guessing based on what a rash looked like online.
What tinea corporis looks like on bare skin
On the body, the fungus behind ringworm (tinea corporis) sticks to the surface, feeding on keratin in the outer skin layer. The textbook look is a round, raised, scaly border with skin that appears close to normal in the center. But that "textbook" look appears only at a certain stage, and skin tone changes how it reads.
On lighter skin, patches tend to look red or pink. On darker skin, they usually show up brown or gray. That distinction is not cosmetic detail, it is diagnostic. Anyone scanning for redness alone on deeper skin tones risks missing the infection.
The rash also evolves in two stages. Early on, it can look like nothing more than a flat, dry, irritated patch, easy to dismiss as ordinary dry skin. As it grows, the ring shape emerges: the center may clear while the border stays raised, scaly, and active. Symptoms appear 4 to 14 days after exposure, so the timeline between contact and visible rash is short but not immediate CDC.
Location on the body changes the picture too. This crusted or pus-filled appearance is specifically noted for ringworm affecting the face and neck https://my.clevelandclinic.org/health/diseases/4560-ringworm. Ringworm on the face and neck can show up crusted over or filled with pus rather than following the clean ring pattern, and the groin version, commonly called jock itch, may never form a complete ring at all. Severity spans a wide range, from mild scaling to blistering, weeping, or crusted lesions, especially if a bacterial infection sets in on top of the fungal one. One thing stays constant on bare skin, though: no hair loss and no bald patches, because the infection never reaches the follicle.
How the presence of hair shafts transforms the infection's appearance on the scalp
Here is the mechanism that explains everything that follows. On skin, the fungus stays on the surface. On the scalp, dermatophytes from the Trichophyton and Microsporum genera burrow into the hair shaft itself and the follicle beneath it. That is not a minor difference, it is the whole story.
Because the fungus lives inside the hair rather than just on the skin around it, what a person sees is damage to the hair. The shaft weakens under fungal invasion until it snaps, which produces the broken-hair signs that define scalp ringworm visually. That single mechanical fact, hair shafts breaking rather than skin merely scaling, is why scalp ringworm looks so different from body ringworm even though the same fungal family causes both.
It also explains something people often get wrong at the drugstore: no topical cream penetrates deep enough into the hair shaft to reach an infection housed inside it. That point deserves its own section later, but the biology behind it starts with the fungus living somewhere creams simply cannot go.
The two main visual patterns tinea capitis produces
Body ringworm mostly sticks to one look. Scalp ringworm does not. It splits into two distinct visual subtypes, and telling them apart says something about how the infection is behaving.
The gray patch type appears as localized or spread-out scaling paired with bald patches, often large and circular, with dull, grayish skin where the hair used to be. Because it can resemble severe dandruff or seborrheic dermatitis at a glance, it is a common source of delayed diagnosis. People treat it like a scalp condition rather than a fungal infection, and the actual cause goes unaddressed.
The black dot type looks different up close. Medscape describes infected hairs as breaking off sharply at the follicular orifice, leaving a conidia-filled stub or black dot https://www.sciencedirect.com/topics/medicine-and-dentistry/tinea-capitis. Bald or thinning areas appear studded with small black dots, which are the broken stumps of hair shafts that snapped off at or near the scalp surface. Looking closely reveals that the scalp itself often appears scaly and silvery around those dots. Of every visual sign scalp ringworm produces, those black dots are the most distinctive, the one detail that separates this condition from anything happening on skin alone.
Both subtypes share some ground: itchiness, scaling, and patches that slowly expand over time. Swollen lymph nodes near the affected area can also show up with scalp ringworm, something that does not happen with uncomplicated body ringworm, and that swelling is a meaningful clue when trying to tell the two apart. Age matters here too. Scalp ringworm is primarily a disease of children ages 3–14, and toddlers and school-age children are the highest-risk group. Adults get it far less often, which is itself a useful piece of information when sizing up a scalp rash.
Kerion: appearance and signs of a medical emergency
Untreated or undertreated scalp ringworm has an endpoint that body ringworm simply does not: kerion. This is the severe inflammatory stage, and it looks nothing like a scaly patch.
Picture soft, raised swellings that actively drain pus, thick yellow crusting across the scalp, hair that falls out or pulls free with almost no resistance, and tenderness that makes the area painful to touch. The mechanism behind kerion is the immune system's overreaction to the infection rather than a simple matter of "more fungus."" It is an overreaction of the immune system responding to the infection. The inflammation looks so much more dramatic than a typical fungal rash as a result.
The consequence is what separates this from every other visual sign discussed so far. Kerion can leave scarring and permanent hair loss behind, a risk body ringworm never carries. So the practical rule is straightforward: swelling, draining fluid, or acute scalp pain moves a case out of wait-and-see territory. That combination calls for prompt evaluation.
Skin conditions that mimic ringworm
On bare skin, ringworm shares visual space with a handful of other conditions: nummular eczema, tinea versicolor, pityriasis rosea, psoriasis, allergic contact dermatitis, granuloma annulare, and, on rare occasions, early Lyme disease. Each produces a round or scaly patch that can, at a glance, resemble a fungal ring.
On the scalp, the most common source of confusion is psoriasis. Both conditions produce scaly, round patches and both can cause temporary hair loss, and that overlap gets them mixed up. But the visual details diverge once someone looks closely. Psoriasis tends to form thick plaques covering the entire lesion, with scales that stick firmly and can bleed if picked at; it is not contagious, and it never produces the black-dot sign. Tinea capitis, by contrast, shows a raised, scaly edge around a center that looks close to normal, comes with black dots from broken hairs, and spreads through contact or shared objects like combs and hats. Scalp psoriasis can also appear red, purple, or brown depending on skin tone, the same tone-dependent variation that complicates ringworm recognition in the first place.
One trap deserves specific mention: applying an over-the-counter steroid cream to what looks like ringworm can calm the visible signs temporarily while making the underlying infection worse and distorting how the rash looks later. Dermatologists call this tinea incognito, and it is a direct consequence of guessing wrong and treating based on that guess. Given how many conditions can mimic ringworm's appearance, visual identification alone carries real limits. Clinicians lean on tools like KOH preparation, fungal culture, and dermoscopy to confirm a diagnosis rather than relying on eyesight, which says something important about how much confidence a mirror check alone deserves.
Why where the infection lives determines which treatment can reach it
The treatment path splits along the exact same line as the visual differences: where the fungus lives. On skin, over-the-counter topical antifungals such as clotrimazole, miconazole, terbinafine, and tolnaftate serve as the appropriate first-line approach. Topicals clear most mild body ringworm cases outright, and if there is no improvement after roughly two weeks, moving to a prescription-strength or oral medication is the reasonable next step.
Scalp ringworm does not respond to that same approach, and the reason traces straight back to the biology covered earlier. Because the fungus lives inside the hair shaft, topical antifungals cannot reach it. Oral prescription antifungals are required. Creams, lotions, and powders will not cure it, full stop. Medicated shampoos have a role, but only in reducing transmission to others, not in treating the infection itself.
Even among oral options, the right choice depends on which fungal species is involved. A retrospective study following 456 pediatric patients found terbinafine achieved complete clinical clearance in 95% of cases involving T. tonsurans, compared with 68% for fluconazole and 38% for griseofulvin PMC. For a different species, M. canis, the numbers flip: griseofulvin and fluconazole performed comparably, at 73% and 66% respectively PMC. Since Trichophyton causes more than 89% of tinea capitis cases in the US, terbinafine tends to be a reasonable first-line oral choice for patients without recent international travel, though that decision belongs to a prescribing clinician who can weigh species and history together PMC. And with drug-resistant strains already spreading globally, accurate diagnosis carries more weight now than it once did, precisely because guessing wrong wastes time against a moving target.
When a visual read is enough to act on
So when does looking in the mirror actually tell someone enough to act? A classic ring-shaped rash on bare skin, in an adult with mild symptoms and no prior steroid cream applied, is a reasonable candidate for a short trial of an OTC antifungal. That is the scenario where a confident visual read carries real weight.
Plenty of situations call for a different response, though. Any scalp involvement, black dots, bald patches, or visibly broken hairs, means OTC topicals will not work and using them anyway only delays the right treatment. Signs of kerion, pus drainage, acute pain, thick crusting, demand prompt evaluation, since treatment may need to combine oral steroids with antifungals. A rash that fails to improve after an OTC trial, keeps spreading, or looks different after a steroid cream was applied also belongs in front of a clinician rather than back on a shelf of creams. Children with any scalp patches deserve a diagnosis before treatment starts, given how much age narrows the odds toward tinea capitis in the first place. And genuine uncertainty, not knowing whether a rash is ringworm, eczema, psoriasis, Lyme disease, or granuloma annulare, is itself a reason to get it checked rather than guessed at.
Clinicians bring tools that close the gap a visual read cannot: KOH preparation, fungal culture, dermoscopy, and Wood's lamp examination all resolve ambiguity that the naked eye leaves open. Culture results can take weeks to come back, so getting evaluated early matters rather than waiting to see how a rash develops on its own. Understanding these visual differences was never really about diagnosing yourself with total confidence. It is about describing what is actually showing up, accurately, to someone equipped to confirm it, and knowing which signs mean the situation needs faster attention than others. Cases where a confident visual read may support an OTC trial.
Sources
- Ringworm (scalp): How to treat this skin condition-Ringworm (scalp) - Symptoms & causes - Mayo Clinic
- Scalp Psoriasis vs. Ringworm: How to Tell the Difference
- Clinical Overview of Ringworm | Ringworm | CDC
- Ringworm (Tinea Corporis): What It Looks Like, Causes & Treatment
- Ringworm (tinea)
- Tinea Capitis - an overview | ScienceDirect Topics
- Tinea capitis: observations and clinical approach in a pediatric population of 99 cases
- Kerion: Symptoms, Causes & Treatment