Pityriasis Alba Versus Vitiligo Visual Differences
Learn the six visual markers that reliably distinguish these two pale-patch skin conditions.
Two skin conditions cause pale patches that look, at a glance, almost identical. Pityriasis alba (PA) and vitiligo both lighten skin, both show up on the face and arms, and both send worried parents or patients searching for answers online. But one clears up on its own within a year or so. The other is a chronic autoimmune disease that needs ongoing management. Telling them apart matters, and the good news is that once you know what to look for, the differences are more reliable than they first appear.
What is happening in the skin in each condition
Pityriasis alba is generally considered a mild form of atopic dermatitis, the same family of skin inflammation behind eczema. The melanocytes, the cells that make pigment, are still there. They're just not working at full capacity. Inflammation and a weakened skin barrier seem to interfere with how much pigment those cells produce and pass along to the surrounding skin. Nobody has pinned down an exact cause, but it isn't contagious and there's no infection driving it.
PA tends to move through three stages, and each one looks a little different. It often starts as a slightly red, raised patch (the erythematous stage), then turns scaly and lighter (scaly hypochromic), and finally settles into a smooth, pale patch with no scale left (smooth hypochromic). If you catch it early, you might see redness. Catch it late, and you're just looking at a soft, faded patch of skin.
Vitiligo works on a completely different mechanism. It's autoimmune: the immune system actively targets and destroys melanocytes, wiping them out rather than just slowing them down. There's a genetic component, and vitiligo occurs more often alongside other autoimmune conditions, including thyroid disease and type 1 diabetes. Research also points to overactivity in the JAK signaling pathway as a driver of the inflammation that fuels the disease (more on why that matters later, when Opzelura enters the picture).
One clinical clue associated with vitiligo is the Koebner phenomenon, where new patches form at sites of skin injury, like a scrape or a cut. That finding carries real diagnostic weight when it appears.
PA is functional impairment, partial and soft-edged. Vitiligo is cell death, complete and sharp-edged. Every visual difference between the two traces back to that one mechanistic split.
The six visual features that separate PA patches from vitiligo patches
1. Degree of pigment loss. This is the most decisive cue, so start here. PA patches are incomplete, off-white or faintly pink, never fully colorless. Vitiligo patches are stark white, with no pigment left. If a patch still has some tone to it, that's a point in PA's favor.
2. Border sharpness. PA patches fade gradually into the surrounding skin; the edges are blurry and hard to pin down. Vitiligo patches have a clean, sharp line, almost like someone traced the border with a pen. Border clarity tracks directly with how much pigment cell loss has occurred; total loss makes a crisp edge, partial loss makes a smudged one.
3. Texture and scaling. PA patches, especially early on, are often round or oval with a mild scale, and the skin feels slightly rough to the touch. Vitiligo patches are smooth. That makes sense once you remember the mechanism: in vitiligo, only the pigment cells are gone, and the skin's surface structure stays intact. So scaling is a PA-only finding. If you see a white patch with any scale on it, that should raise real suspicion against vitiligo, not for it.
4. Body distribution. PA appears mostly on sun-exposed areas: the cheeks, arms, neck, and upper trunk. Vitiligo also likes the face, but it tends to center around the eyes and mouth, and it frequently appears on the hands, feet, genitalia, and areas of repeated friction like knees and elbows, places PA rarely touches. A white patch on the hands or genitals should shift your thinking toward vitiligo pretty firmly.
5. Symmetry. PA patches do not share the bilateral mirroring seen in vitiligo. Vitiligo patches often appear on both sides of the body symmetrically, a hallmark of its systemic, autoimmune nature.
6. Effect of sun exposure. Both conditions become more visible once surrounding skin tans, but the reason differs. In PA, the healthy skin around the patch darkens normally in the sun; the patch itself doesn't repigment well, so the contrast gets worse. In vitiligo, there are no melanocytes left to respond to UV light at all, so the patch just sits there, whiter against darker, tanned skin. Sun exposure just makes both conditions easier to see, without diagnosing which one it is. It just makes both conditions easier to see and, unfortunately, harder to feel good about.
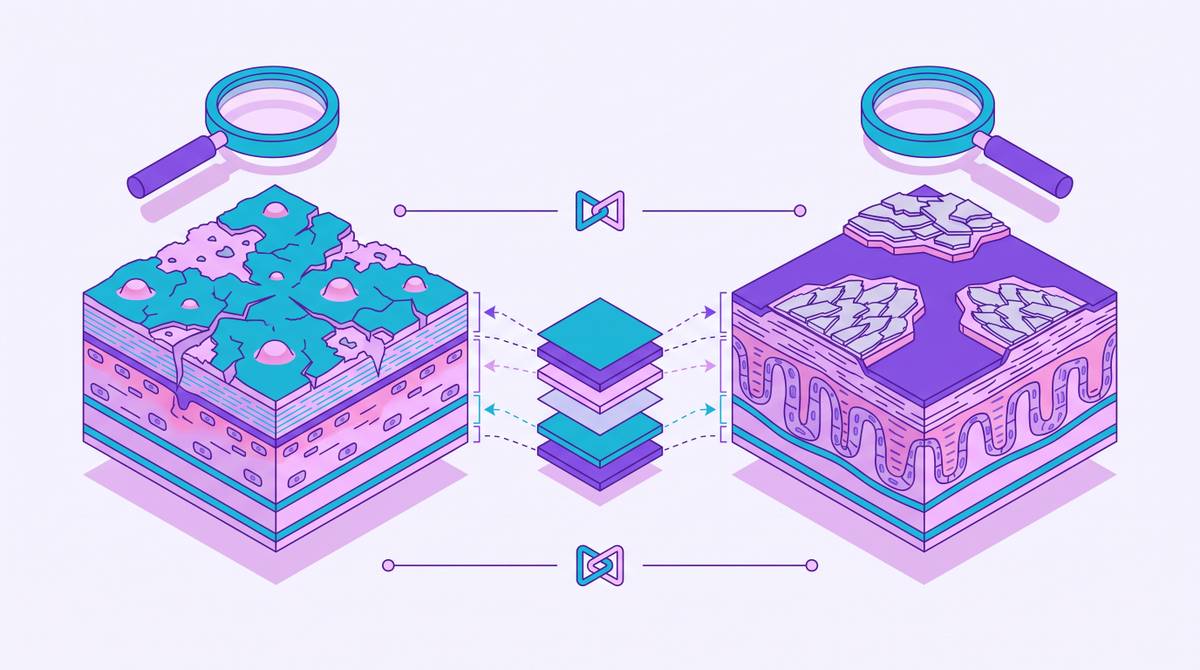
Picture a simple six-row comparison, side by side: appearance, border, texture, location, symmetry, and sun response. Laid out that way, the pattern becomes obvious fast, which is the point of learning these six markers.
Who tends to get each condition
Age is doing a lot of work here. PA overwhelmingly affects children between 3 and 16, and roughly 90% of cases occur in kids younger than 12. An estimated 5% of children in the United States may have it at some point, and it affects boys and girls in roughly equal numbers.
There's also a documented disparity by skin tone. One pediatric atopic dermatitis cohort found PA in 28% of patients overall, but that broke down to 47% among skin-of-color patients versus 15% among non-skin-of-color patients (NCBI PMC10862149). Hypopigmentation simply reads more visibly on darker skin. It's both more likely to be noticed and, unfortunately, more likely to get mislabeled without a careful look.
Vitiligo's age profile runs differently. Global prevalence is between 0.2% and 1.8% (NCBI PMC12390786), and while it can start at any age, it is not confined to childhood the way PA is. It appears in kids too, just far less often than PA does.
Vitiligo carries a psychological weight. Even though it doesn't damage tissue or cause pain, its psychosocial burden runs parallel to chronic conditions like psoriasis and eczema. Documented rates of stigma, anxiety, and depression run especially high when patches appear somewhere visible: the face, neck, or hands.
Putting age and location together produces a useful shortcut. A pale cheek patch on a dark-skinned child under 12 points strongly toward PA. Symmetric white patches around the eyes, or on the hands, in an adult push the odds toward vitiligo instead.
How a dermatologist confirms which condition is present
In plenty of straightforward cases, a dermatologist doesn't need equipment. Pattern, history, and age of onset narrow things down fast on clinical exam alone.
When the picture isn't clean, the Wood's lamp becomes the deciding tool. It emits long-wave UVA and violet-blue light, and it makes pigment loss visible in a way that ordinary room light doesn't. Under the lamp, PA patches might look a bit more obvious, but they stay non-fluorescent, consistent with melanocytes that are impaired but present. Vitiligo patches fluoresce brighter, and the edges snap into sharper focus, consistent with melanocytes that are simply gone. This one instrument often settles a question that the naked eye can't.
Biopsy comes into play for uncertain vitiligo cases, confirming the outright absence of melanocytes under the microscope. It isn't routine for PA. A 2025 global vitiligo guideline referenced on Medscape recommends biopsy, mycologic exam, and relevant blood work when the diagnosis is unclear, along with routine screening of thyroid antibodies and thyroid function given how often vitiligo travels with autoimmune thyroid disease.
Dermatologists also have to rule out a short list of look-alikes. Tinea versicolor, caused by Malassezia yeast, tends to sit on the upper trunk and glows yellow-green under a Wood's lamp, a fluorescence pattern distinct from both PA and vitiligo. Nevus depigmentosus is congenital, present from birth, stable in size, and often follows a segmental pattern on the trunk. Idiopathic guttate hypomelanosis shows up as small, pearly spots on sun-damaged skin in older adults, and age plus that specific appearance usually gives it away. PA, vitiligo, nevus depigmentosus, and tinea versicolor are among the most common causes of hypopigmentation seen in children.
The visual cues covered earlier genuinely help narrow the field. But when a patch doesn't fit neatly into one bucket, that's exactly the situation where a Wood's lamp exam, not another round of squinting at it in the mirror, settles the question.
An observational study that complicates the clean boundary between the two conditions
A case-series study by Sharquie and colleagues, published in the Journal of the Saudi Society of Dermatology and Dermatologic Surgery in 2013, looked at 134 PA patients between ages 2 and 15 (mean age 7.9, plus or minus 3.3 years) to test whether PA might sometimes progress into vitiligo rather than resolve on its own.
Among the full group, 19.4% had a family history of vitiligo. Among the full group, 19.4% had a family history of vitiligo. And 14.17% of patients had PA and vitiligo lesions present at the same time, and within that overlapping group, 57.89% had a positive family history of vitiligo. Among the smaller subset, 23.88% of the original cohort, who completed follow-up, 43.75% saw their original PA lesion progress into vitiligo. Of that follow-up group, 34.35% showed a positive Koebner phenomenon, and 31.25% had a family history of vitiligo.
Remember that Koebner sign from earlier? It's a vitiligo feature, not a PA one. So seeing it show up in a PA patient, especially one with a family history of vitiligo, is a signal to watch, not ignore.
What does this mean in practice? For most kids, PA is a self-limited eczema variant that clears up and moves on. But for a subset, particularly those with vitiligo already running in the family, PA may sit closer to an early or overlapping presentation of the autoimmune process than a fully separate condition. It's a reason for follow-up, especially when family history or Koebner's sign is part of the picture. It's a reason for follow-up, especially when family history or Koebner's sign is part of the picture.
What treatment looks like for each condition, given how differently they work
PA gets managed conservatively, because it resolves on its own. Most cases clear up within roughly a year, though some linger longer. First-line care is mostly about comfort and patience: reassurance, a low-potency topical steroid like hydrocortisone 1% or desonide 0.05% to calm redness and itching, and bland emollients to cut down on scaling, particularly on the face. Sun protection matters too, since it keeps the surrounding skin from tanning and making the patch stand out more.
Topical tacrolimus gets used off-label sometimes, but no single treatment has been shown to clearly outperform the rest. Steroid use should include regular breaks, since long stretches on the face can thin the skin.
Vitiligo asks for something entirely different, because it doesn't resolve without treatment and tends to progress if left alone. Topical calcineurin inhibitors, tacrolimus and pimecrolimus, are used off-label as first-line therapy, and they tend to work better on the face and neck than on hands and feet. They help by encouraging melanocytes to multiply and migrate back into the depigmented area. UVB phototherapy is another established option for stimulating repigmentation.
Then there's ruxolitinib cream, sold as Opzelura, the first and only FDA-approved topical treatment for repigmentation in nonsegmental vitiligo, cleared for patients 12 and older. It's a topical JAK inhibitor, and it works by targeting that same JAK signaling pathway mentioned earlier as a driver of vitiligo's inflammation. The approval rested on the Phase 3 TRuE-V1 and TRuE-V2 trials, which enrolled more than 600 participants with nonsegmental vitiligo covering 10% or less of total body surface area. At 6 months, 29.9% of patients using ruxolitinib cream hit a 75% improvement in facial vitiligo area scores across the two trials, compared with 7.5% and 12.9% in the groups using a non-medicated cream. Some patients need more than 24 weeks to see a satisfactory response, and the approval covers treatment areas up to 10% of body surface. Pregnancy data is limited, so patients who are or might become pregnant need direct counseling and should report any exposure through the designated registry.
For stable, extensive vitiligo, additional specialist-directed options exist beyond topical and light-based therapies, depending on the severity and distribution of disease.
The contrast in treatment mirrors the contrast in mechanism almost perfectly. PA care is supportive and finite. Vitiligo care is targeted, ongoing, and now includes an approved therapy built specifically around the pathway driving the disease.
How AI-assisted clinical tools are changing how pale patches are assessed
Measuring a vitiligo patch consistently is harder than it sounds. Borders can be irregular, contrast against surrounding skin varies by lighting and skin tone, and two clinicians measuring the same patch by eye won't always land on the same number. That inconsistency has made lesion tracking, and by extension clinical trial endpoints, a persistent headache.
A paper in Frontiers in Medicine, from a team at the University of Padua led by Mazzetto and colleagues, looked at automated image analysis as a way to standardize how vitiligo lesions get measured. The goal is giving clinical judgment a more consistent yardstick. It's giving that judgment a more consistent yardstick, addressing the same kind of visual ambiguity, irregular edges, variable contrast, that makes distinguishing PA from vitiligo tricky. If that kind of tool matures, it could tighten up how progression and treatment response get tracked over time, which matters most for a disease that, unlike PA, doesn't resolve on its own and needs to be watched closely.