Dermatofibroma Appearance and Distinguishing Features
These common benign skin bumps have distinctive textures and a telltale dimple.
A dermatofibroma is a benign skin tumor, sometimes labeled a fibrous histiocytoma, and it occurs far more often than most people assume. Roughly 3 out of every 100 skin lesions evaluated turn out to be one, which puts it well outside rare-finding territory. That number almost certainly undercounts the real total. Most dermatofibromas cause no symptoms, and plenty of people carry one for years without ever mentioning it to a doctor. A lesion nobody flags never makes it into anybody's statistics, so the true rate is probably higher than the charts suggest.
Adults between 20 and 49 develop these most often.
What a dermatofibroma looks like at a glance
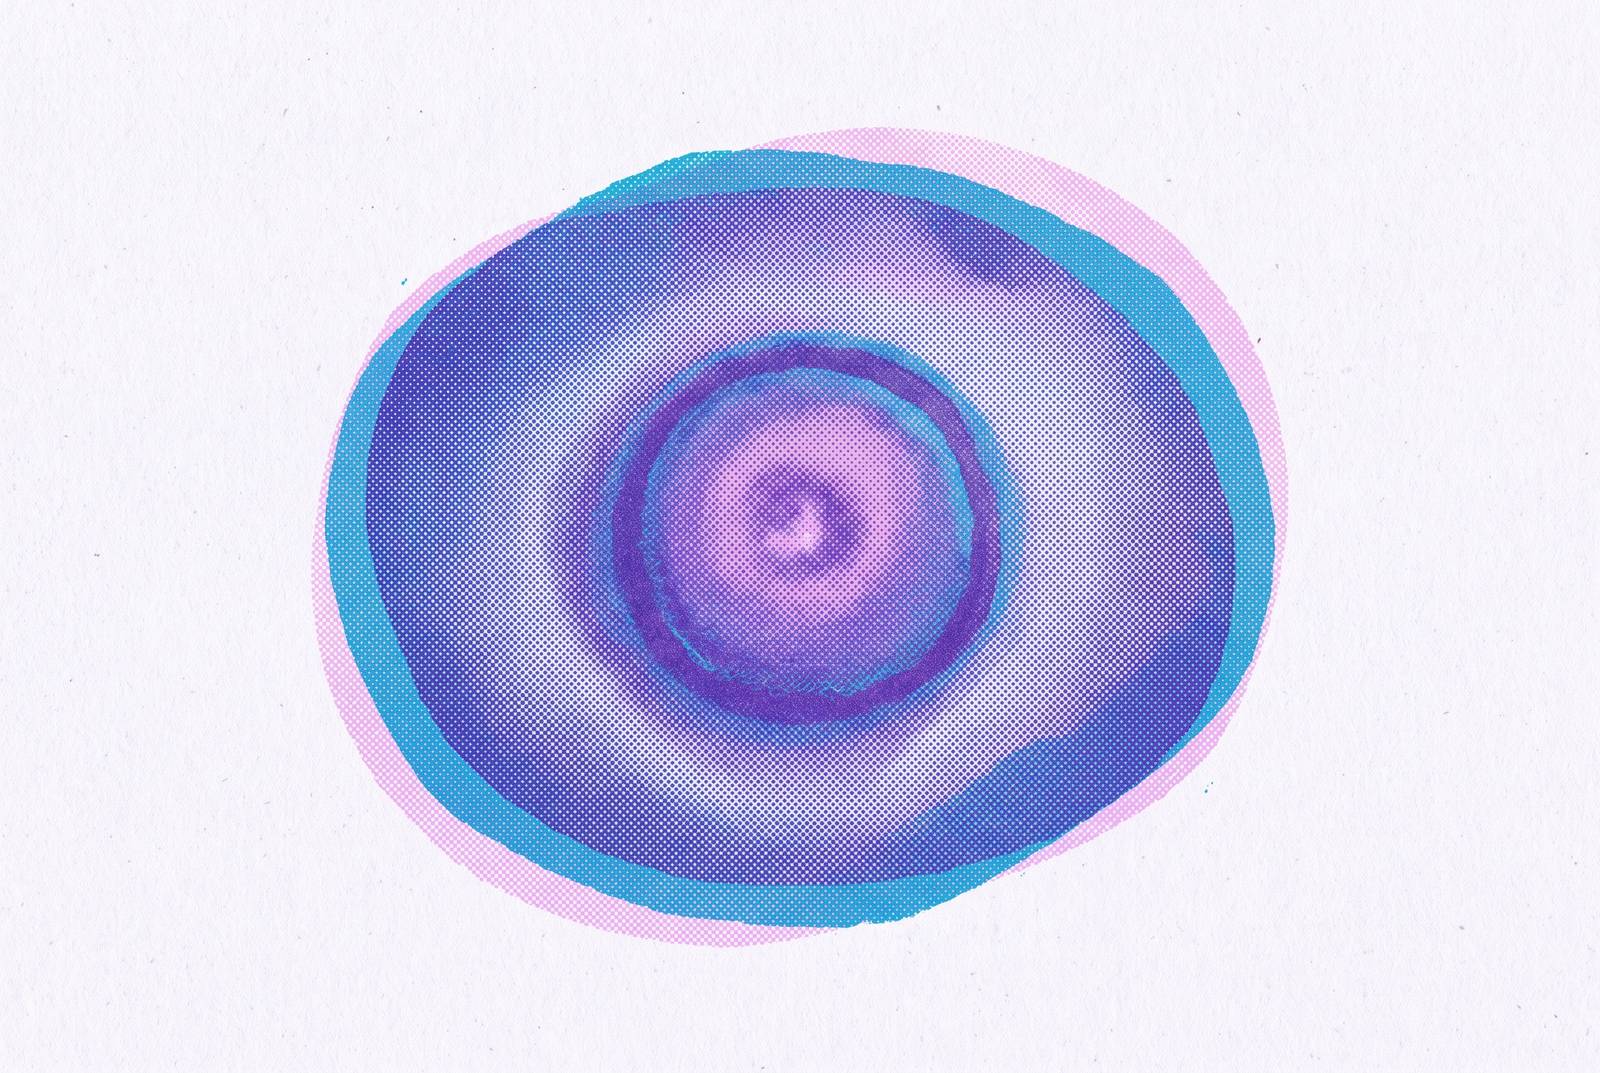
Look for a small, firm bump, round to oval, dome-shaped, with edges sharp enough to trace with a fingertip. Once a lesion balloons past a centimeter, it has already stepped outside the typical range and deserves a second look.
Color is where dermatofibromas get unpredictable. They can show up flesh-colored, gray, yellow, orange, pink, red, purple, blue, brown, or black, sometimes several blended together, though tan to brown is what shows up most. The center often runs darker than the rim, fading outward toward the border. Not every lesion follows that pattern exactly, but when it does, it is a useful visual signature to bank on.
How a dermatofibroma feels when you touch it
Touch gives it away faster than sight does. Dermatofibromas feel distinctly firm, almost hard, and people often compare the sensation to pressing on a small stone or pebble lodged just under the skin.
The lesion stays fixed to the skin above it, so you can't slide the surface over it the way you could with a cyst or a fatty lump. It does move over the deeper tissue underneath, though, which is a specific, in-between quality: not glued down at every layer, not floating free either. That fixed-but-movable feel doesn't belong to any other common skin lesion, which makes it a genuinely useful clue on its own, before a clinician even reaches for a tool.
Most dermatofibromas cause no symptoms. But itching and tenderness get reported often enough, and dermatofibromas are actually among the most common painful skin tumors encountered clinically, so pain by itself doesn't rule anything out. It's just one more way these lesions can present, and clinicians who dismiss a tender bump as "probably something else" because dermatofibromas are "supposed to be painless" are working off an incomplete picture.
The dimple sign and negative result significance
Pinch the skin gently on either side of the lesion. A dermatofibroma will dimple or sink inward at the center instead of bulging up or sitting flat, a response clinicians call the dimple sign, also known as the Fitzpatrick sign.
The mechanism is mechanical, once you see it, it's obvious: the growth is tethered down into the tissue beneath it, so squeezing from the sides pulls the center downward instead of letting it pop outward. That's why the pinch test earned its spot as a standard bedside step alongside the visual exam.
A negative result, where the center doesn't dimple, still leaves a dermatofibroma on the table as a possible diagnosis. It isn't a yes-or-no test by itself. Combined with other atypical features, though, a flat response to the pinch is one more reason for a clinician to slow down and look harder rather than sign off on the easy answer.
What happens inside the skin to produce this nodule
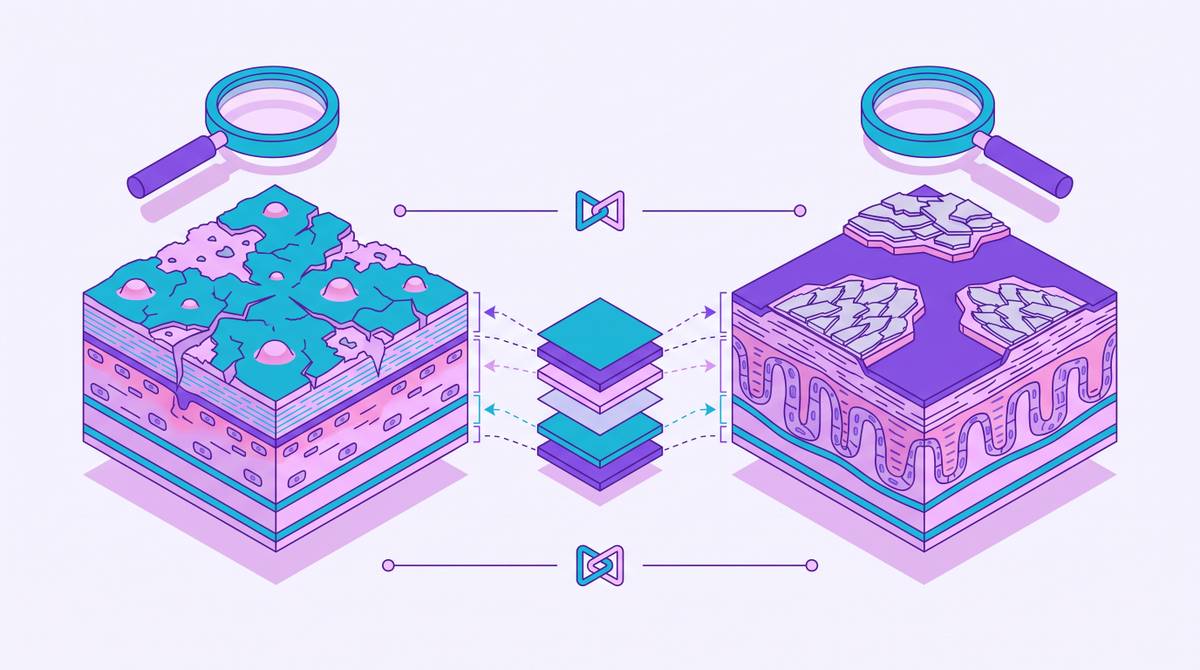
Putting a dermatofibroma under a microscope reveals a cluster of spindle-shaped fibrocytes, a type of fibroblast, and histiocytes packed inside a stroma thick with collagen. The epidermis above thickens, the base layer darkens with extra pigment, and a distinctive rim of thickened epidermis, sometimes called a collarette, often wraps around the lesion's edge.
Histiocytes persist and multiply abnormally, while fibroblasts pile up and overproduce fibrous tissue. That combination builds the firm little nodule you can feel from the outside, and it explains the dimple sign mechanically: all that extra collagen doesn't just harden the lesion, it tethers it to the tissue below. Pinch the sides, and the center has nowhere to go but down. Once you understand that tethering, the dimple sign stops looking like a party trick and starts looking like a physical consequence of the tissue underneath.
Why dermatofibromas develop and who is more likely to get them
Why do these form? That's still genuinely debated, and the honest answer is that most of the time, nobody can point to a cause. One camp treats dermatofibromas as reactive, the skin overcorrecting after some local injury. Another treats them as spontaneous growths that need no external trigger.
The evidence favors the second camp more than most people assume. Most dermatofibromas occur with no identifiable cause behind them, so spontaneous development is the norm. Hunting for a backstory, an old bug bite, a nick from shaving, on every single lesion is often a dead end and gives patients false confidence that they can trace and prevent these things. The trauma theory holds up in a meaningful minority of cases, but it stays a minority, and treating it as the default explanation overstates what the data actually supports.
Frequent shaving or waxing, and insect bites from time spent outdoors, are among the minor traumas sometimes cited as possible triggers. Neither one guarantees anything, and plenty of people with none of those exposures develop dermatofibromas anyway, which is really the whole point: this is a condition you can't reliably predict or prevent your way out of.
Variants that can look or behave differently from a typical dermatofibroma
The textbook description doesn't hold for every case. Among lesions sent for detailed pathology review, roughly 20% turn out to be one of the rarer variants, a share high enough that these subtypes deserve real attention instead of a footnote. Named variants include lipidized, aneurysmal, hemosiderotic, cellular, clear cell, atrophic, epithelioid, and sclerotic forms.
One variant carries more clinical weight than the rest: cellular dermatofibroma, or CDF. It tends to grow deeper, reaching into subcutaneous tissue instead of staying near the surface, and it behaves more aggressively than the typical lesion does. In rare cases, it can even metastasize. None of that matches the profile of a typical dermatofibroma, so CDF gets flagged for closer follow-up rather than treated as business as usual. Anyone reading "dermatofibroma" on a pathology report should ask, specifically, whether the cellular subtype was ruled out. That single question changes the follow-up plan.
Atypical presentations depart sharply from the small, stable, symptom-free picture most people associate with these lesions. That departure is the whole reason histopathological confirmation stops being optional the moment the clinical picture doesn't add up.
Lesions that can look like a dermatofibroma
A handful of other skin lesions mimic a dermatofibroma closely enough to cause real diagnostic uncertainty. One of them, dermatofibrosarcoma protuberans, or DFSP, is malignant, so mistaking it for a dermatofibroma can delay treatment of a cancer. It shows up as a firm nodule, often on the trunk, and at a glance it can look almost identical. Getting this one right is not a matter of academic precision, it separates reassurance from a missed cancer diagnosis.
Melanoma is another lookalike, especially in darker or unusual presentations where color variation muddies the picture. If a lesion is ulcerated or looks infected, squamous cell carcinoma or atypical fibroxanthoma enter the conversation as well.
So how do clinicians actually tell a dermatofibroma and DFSP apart when both present as the same firm nodule to the naked eye? The lab does the real work, not the eye. Dermatofibromas typically express a marker called Factor XIIIa and test negative for CD34. Some focal CD34 positivity can appear in a dermatofibroma, but it stays under 20%, well short of what DFSP shows. That gap in staining pattern is usually what settles the question when the naked eye can't.
Before any lab work, at the bedside, doctors lean on the ABCD rule built for melanoma screening: asymmetry, border irregularity, color variation, and diameter change. Dermatofibromas typically don't trigger these flags, which is itself a useful piece of reassurance. Dermoscopy adds another layer. Under magnification, a classic dermatofibroma shows peripheral reticular pigmentation ringed around a central white spot, and that pattern, paired with the clinical picture, often lets a doctor rule out melanoma without cutting into the skin at all.
Warning signs that a lesion needs prompt clinical evaluation
Start with the reassuring baseline: most dermatofibromas are slow and stable, and staying exactly the same year after year is itself a good sign, maybe the best sign there is.
What should send someone to a clinician faster? Rapid growth is one clear flag. Ulceration or bleeding is another, and so is any change in the lesion that wasn't there before. Asymmetry or ragged, irregular borders belong on that list too, and none of these should wait for a routine annual checkup to get looked at.
A lesion turning painful after months or years of causing no trouble deserves attention, as does new tenderness with no obvious cause behind it. If several new lesions appear within a short stretch of time, that points toward something systemic rather than a single skin question, and it calls for a broader medical look rather than a dermatology visit alone.
A positive dimple sign and a small, stable size are genuinely reassuring signs to have in your favor. Neither one, though, is a reason to skip getting a lesion checked the moment any of these red flags appears.
What the diagnostic tools can show
For most straightforward cases, an experienced clinician makes the call through visual inspection and a solid patient history alone. That's usually where the diagnosis starts, and often enough, where it ends, no biopsy, no imaging, just a trained eye and a pinch test.
The pinch test happens right there in the clinic room, formalizing what's really a simple, low-tech check. Dermoscopy adds magnification: a handheld device lets a clinician examine the surface closely, watching for that same signature pattern centered on a central white area. That pattern has been mapped across four recognized dermoscopic subtypes, and spotting it helps separate a true dermatofibroma from its mimics without cutting into the skin at all.
Biopsy enters the picture only when the clinical read isn't clean. If a lesion bleeds, ulcerates, develops an oddly shaped surface sore, or simply doesn't match up on visual and dermoscopic exam, excisional biopsy becomes the standard next step. Once the margins come back clear, recurrence is rare. That is why clinicians reach for biopsy as a confirmation tool rather than a first move.
Describing a suspected dermatofibroma clearly when seeking care
Walking into an appointment, or sending a message to a provider, with the right details already sorted speeds up the whole process. A few minutes of notes beforehand pays off once the exam starts.
Note the color precisely, including how it shifts from center to edge or stays uniform throughout. Pin down the exact location on the body, and be ready to say when the lesion first appeared and how it has changed since.
Texture matters just as much as appearance. Describing it as "firm like a small pebble" or "hard like a button under the skin" gives a clinician a far clearer starting point than "there's a bump." Don't skip the pinch test either: note whether the skin dimpled inward when gently squeezed from both sides, or whether it stayed flat. Any history of trauma at that spot, an old insect bite, a nick from shaving, a scrape that never quite healed right, rounds out the picture. That detail alone can help a clinician sort out what's likely going on before they have even examined it directly.